
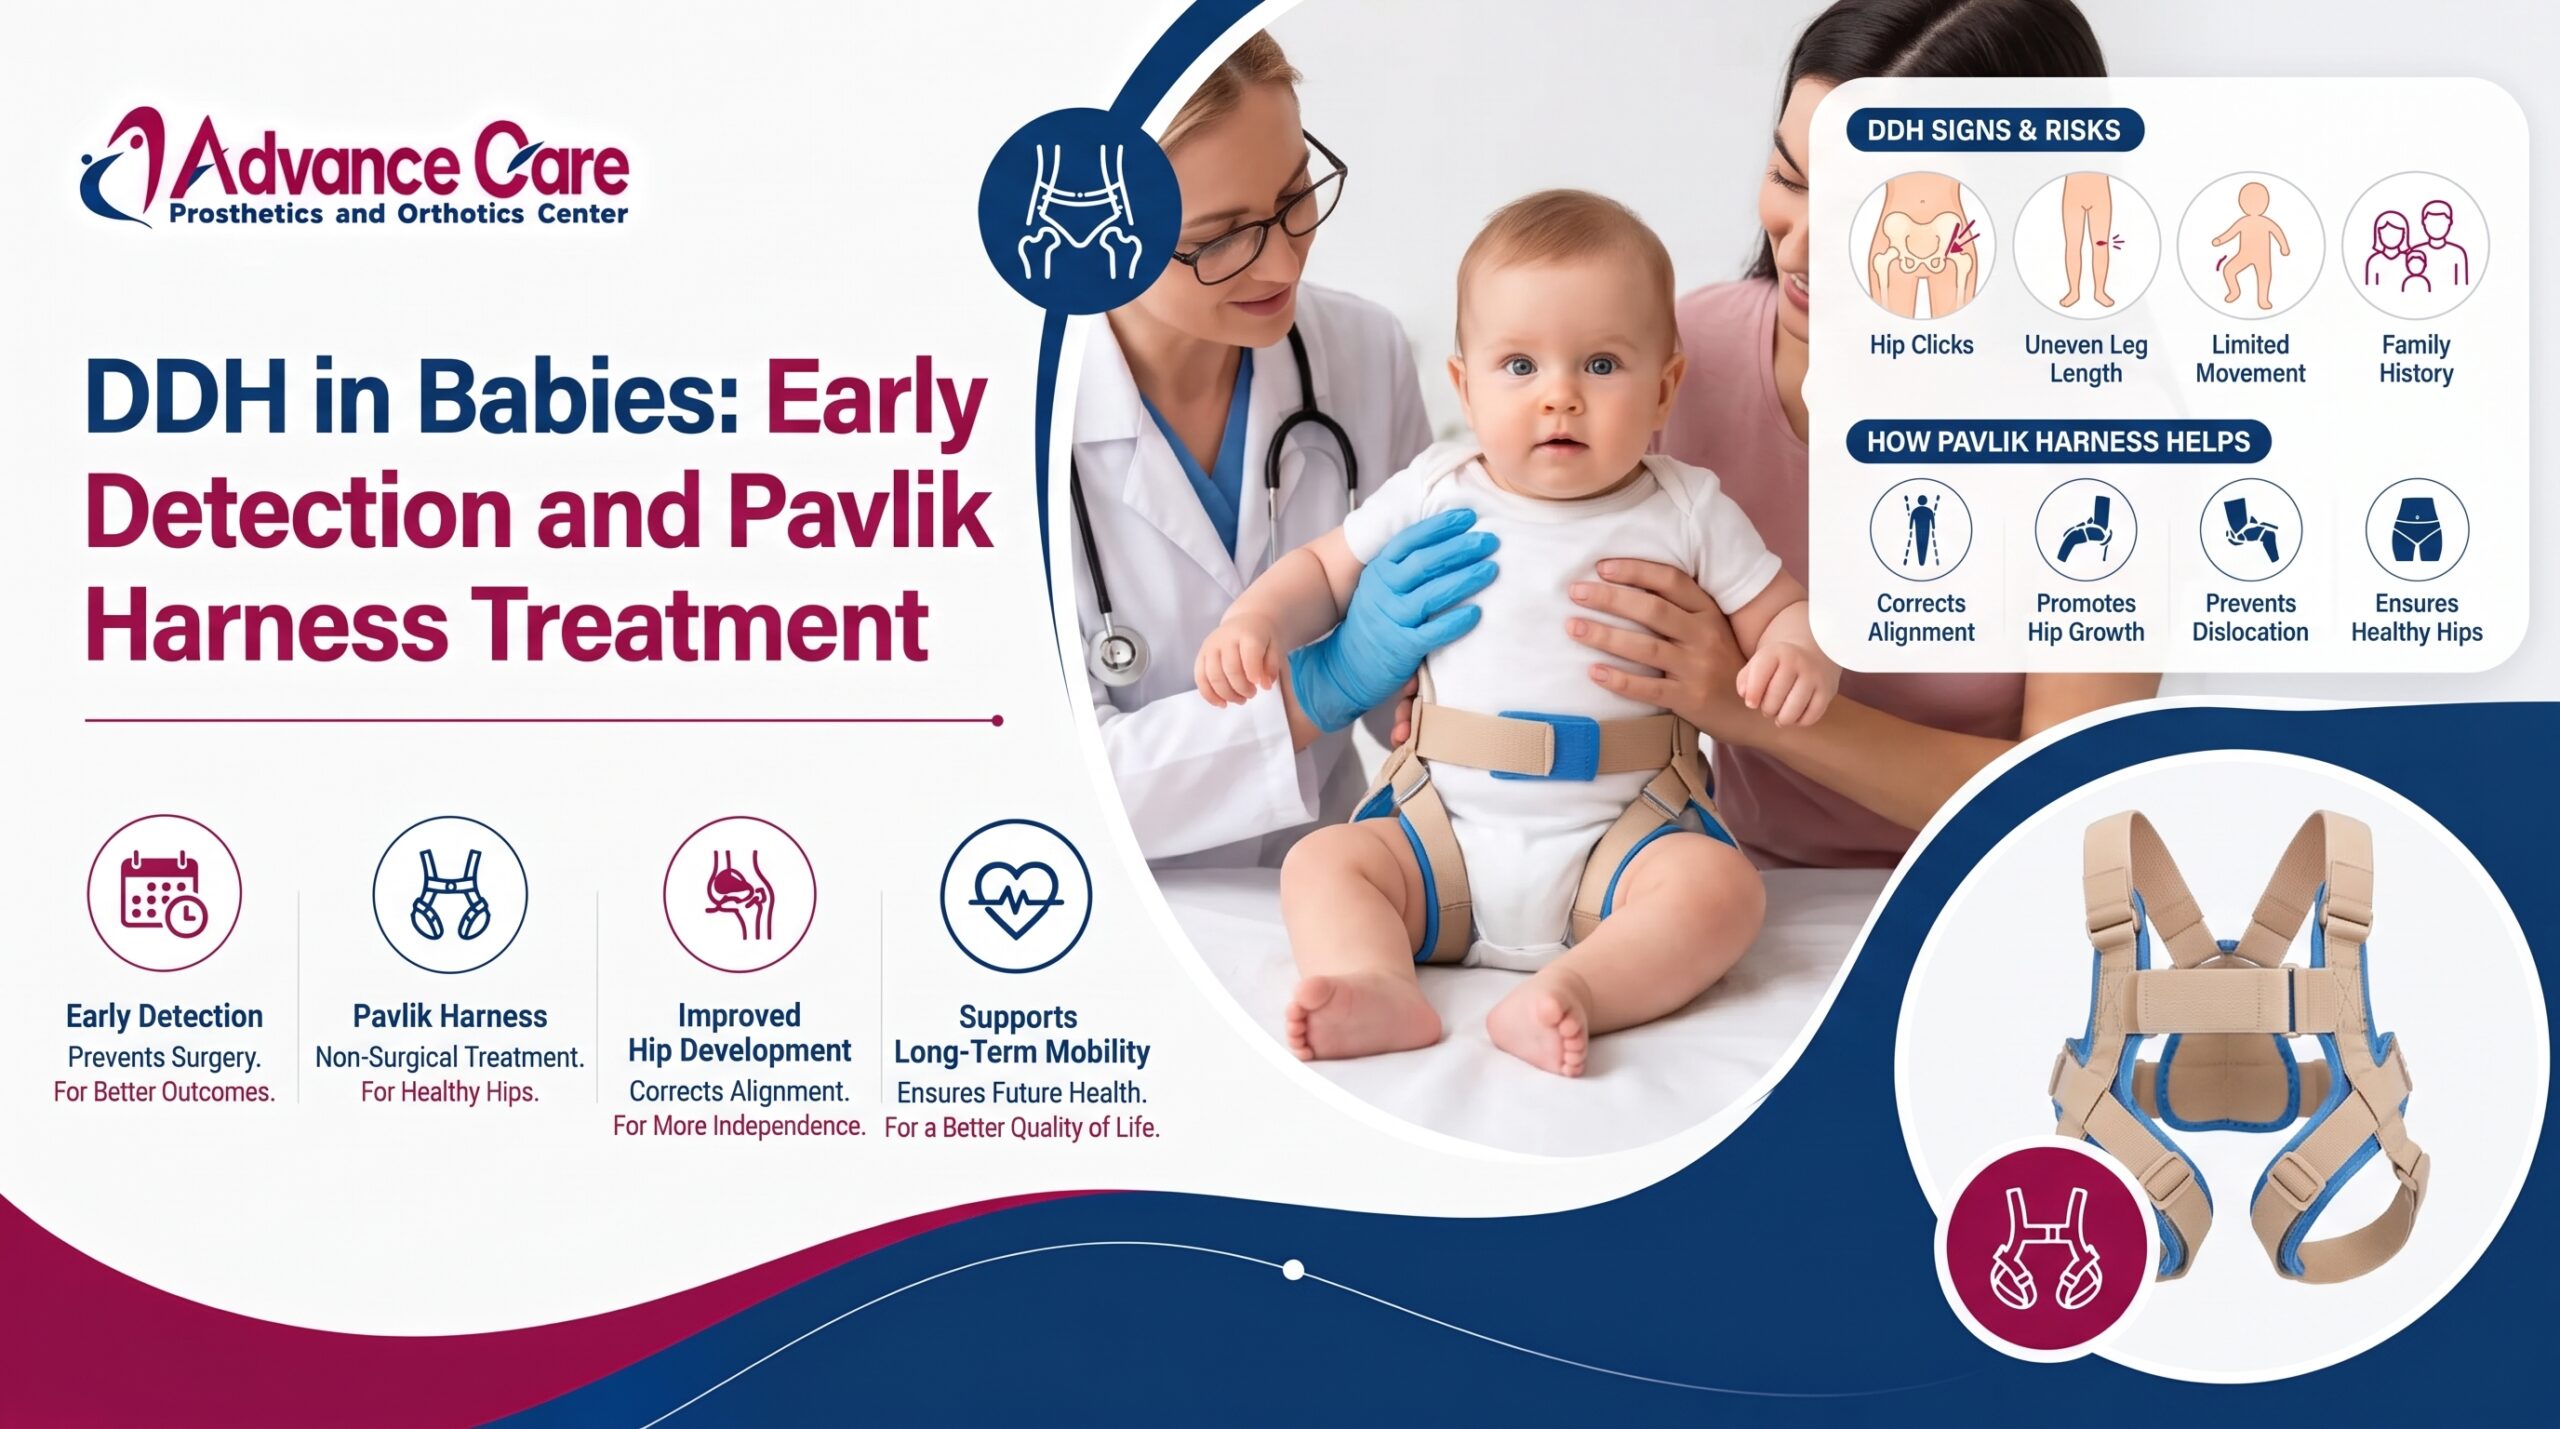
What Is DDH?
Developmental Dysplasia of the Hip (DDH) is a condition in which the hip joint does not develop normally. The femoral head (the ball) may be loose within, partially displaced from, or completely dislocated from the acetabulum (the socket).
Risk Factors
- Female sex
- First-born baby
- Breech presentation
- Family history of DDH
- Limited space in the uterus
Signs and Symptoms of DDH
In Newborns
- Positive Barlow test
- Positive Ortolani test
- Hip instability
- Limited hip abduction
- Difference in leg length
In Older Infants
- Parents may notice unequal thigh or buttock skin folds
- Limited movement of one leg
- One leg appearing shorter
In Walking Children
- Limping
- Waddling gait
- Leg-length discrepancy
- Reduced hip movement
How Is DDH Diagnosed?
- Hip ultrasound is particularly useful in young infants because the hip is not yet fully ossified.
- As the child becomes older, pelvic X-ray becomes increasingly useful.
Safe vs. Unsafe Swaddling
Unsafe: A baby wrapped tightly with legs stretched straight down and pressed together. This pulls the femoral head out of the socket.
Hip-healthy: A swaddle that is snug around the arms but loose and roomy below the waist. The hips should be free to flex up and outward into a natural frog-leg position.
Why Is Early Detection Necessary?
The window closes fast. Treating hip dysplasia at 6 weeks can be as simple as a harness, but at 6 months it requires an operating room.
By the time a child starts limping, the treatment path turns from weeks in a fabric brace to months in a hard body cast.
Treatment of DDH
Treatment depends mainly on:
- The child’s age
- Whether the hip is stable, subluxated or dislocated
- Response to previous treatment
The main principle is to keep the femoral head centered in the acetabulum while allowing the hip to develop normally.
Orthotic Management Provided by Advance Care
1. Pavlik Harness
The Pavlik harness is commonly used in young infants with suitable reducible or unstable DDH. It maintains the hips in flexion and abduction while allowing controlled movement. Controlled movement helps the femoral head remain centered and supports acetabular development.
- Total Duration: Typically 6 to 12 weeks.
- Full-Time Wear: Worn 23 to 24 hours a day for at least the first 6 weeks or until ultrasound imaging shows the hip has fully stabilized.
- Weaning Period: If successful, the baby is gradually transitioned out over an additional 4 to 6 weeks, wearing it only for naps and nighttime.
2. Hip Abduction Orthosis
A hip abduction brace may be used in selected children, particularly when treatment with a harness is no longer appropriate or as part of treatment following reduction. Its purpose is to maintain the hip in an appropriate position and keep the femoral head centered in the acetabulum.
What Happens If DDH Is Not Treated?
Untreated or inadequately treated DDH can lead to:
- Persistent hip dislocation
- Abnormal walking pattern
- Leg-length discrepancy
- Hip pain
- Early degenerative or osteoarthritic changes
- Reduced hip function
Key Message for Parents
DDH is treatable, particularly when identified early.
Parents should not wait for obvious walking problems before seeking assessment. If a baby has important risk factors, especially breech presentation or a family history of DDH, the pediatric or orthopedic team may recommend appropriate screening.
Early detection, early treatment, better hip development.

